What Are Carbs
Carbohydrates are your body’s preferred fuel source, but not all carbs behave the same. This guide breaks down simple vs. complex carbs, how they’re digested, what fiber actually does, and how carbs fit into fat loss, muscle gain, and long-term health. Clear, science-based, and practical.
 makko

Overview
Carbohydrates (often shortened to “carbs”) are molecules made from sugar units that your body can digest into glucose or ferment in the gut, depending on the type. They show up as sugars (like glucose, fructose), starches (like in grains and potatoes), and fibers (like in beans, oats, vegetables). “Carbohydrates explained” in one line: carbs are a broad category, and their health effects depend far more on the specific carb type and food source than on the word “carb” itself.
Carb digestion mostly happens in the small intestine, where enzymes break starches and disaccharides into monosaccharides for absorption. Glucose is tightly regulated because it is a main fuel for the brain and central nervous system and the only fuel for some cells (like red blood cells). When carbs enter the bloodstream, hormones such as insulin help move glucose into tissues and manage storage as glycogen or, when energy intake exceeds needs, fat.
Tools like the glycemic index (GI) and glycemic load (GL) describe how strongly a carb-containing food raises blood sugar. They can be useful, especially for diabetes and endurance sport contexts, but they are imperfect because GI varies with cooking, processing, ripeness, mixed meals, and individual physiology. That is why many guidelines focus on overall patterns: emphasize minimally processed carbs, whole grains, legumes, vegetables, whole fruits, and fiber; minimize refined grains and added or free sugars. ()
For weight management, “carbs and weight loss” is mostly about adherence, calorie balance, protein adequacy, and carb quality. Trials comparing healthy low-fat vs healthy low-carb approaches often show similar average weight loss over 12 months, with wide individual variation. If you do well on lower-carb, it can be a valid option, especially for glycemic control in some people with diabetes, but it is not automatically superior.
What are carbs and carb types
At the chemistry level, carbohydrates are organic molecules built from carbon, hydrogen, and oxygen. Many follow a rough (CH₂O)n pattern, but biology is messy and not every carbohydrate fits the classroom formula neatly. What matters more is structure: carbs are made of sugar units linked together by glycosidic bonds, and the type of linkage (for example, α vs β linkages) changes how a carb behaves in the body. That one detail helps explain why starch can be digestible while cellulose (a plant fiber) largely is not.
When people ask “what are carbs,” they are usually talking about four chemistry-based categories:
- Monosaccharides: single sugar units (e.g., glucose, fructose, galactose).
- Disaccharides: two sugar units linked together (e.g., sucrose = glucose + fructose; lactose = glucose + galactose; maltose = glucose + glucose).
- Oligosaccharides: short chains of sugar units (often discussed in gut health, since many reach the colon and are fermented).
- Polysaccharides: long chains of sugars. Starch and glycogen are glucose polymers used for energy storage; cellulose is a structural polysaccharide in plants and functions as dietary fiber for humans.
Here is a practical way to connect “carb types” to food. Sugars are mostly mono- and disaccharides. Starches are polysaccharides, largely digestible. Fibers are carbohydrates that resist digestion in the small intestine and either pass through (helping stool bulk) or are fermented by gut microbes into short-chain fatty acids (SCFAs).
Digestion and absorption from bite to ATP
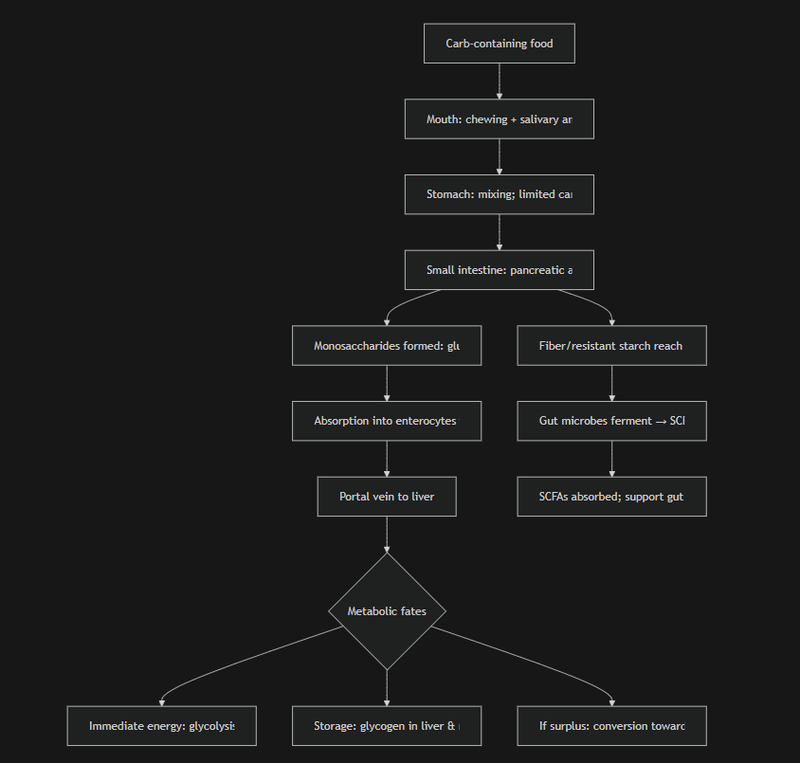
Carb digestion starts in the mouth, where salivary amylase begins breaking down starch. The stomach is mostly a mixing chamber for carbs; most meaningful carbohydrate digestion happens in the small intestine when pancreatic amylase and brush-border enzymes finish the job, turning starches and disaccharides into monosaccharides.
Absorption is where the biochemistry becomes real life. Glucose and galactose are absorbed via sodium-dependent transport (classically SGLT1). Fructose uses a different transporter (classically GLUT5). Under higher carbohydrate loads, transporter expression and localization can shift, changing absorption capacity. This is one reason carbohydrate tolerance varies across people and across eating patterns.
Once absorbed, monosaccharides travel via the portal vein to the liver. The liver plays traffic controller: it converts fructose and galactose into forms that can enter common metabolic pathways (often ending as glucose-derived intermediates), stores some carbohydrate as glycogen, releases glucose to maintain blood sugar, and packages excess energy for longer-term storage.
Then comes energy conversion. Cells can burn glucose immediately (glycolysis followed by oxidative metabolism when oxygen is available) or store it as glycogen in liver and muscle. When energy intake chronically exceeds expenditure, surplus carbohydrate energy can contribute to fat storage, although the exact pathway and magnitude depend on the diet context, insulin dynamics, and overall energy balance.
Glycemic index, glycemic load, and the hormonal response
The glycemic index (GI) ranks carbohydrate-containing foods by how strongly they raise blood glucose compared to a reference (often pure glucose). A common classification is: low GI ≤55, medium 56–69, high ≥70.
The glycemic load (GL) adds real-world context by including quantity. Conceptually: GL combines the quality of carbohydrate (GI) with the amount of available carbohydrate in a typical serving. That is why watermelon can have a relatively high GI but a modest GL per usual portion.
The hormonal response matters because glucose is not just fuel; it is a signal. A faster, higher rise in blood glucose tends to produce higher insulin secretion, and insulin helps tissues take up glucose and suppresses hepatic glucose output. The gut amplifies this insulin response via the “incretin effect” (notably GLP-1 and GIP), meaning the same blood glucose level can trigger more insulin when glucose arrives through the gut compared to intravenous glucose.
Two clarifiers keep GI/GL useful instead of annoying:
GI is not a moral score. It is one numeric property under specific testing conditions. Real meals include fat, protein, fiber, acids, and different cooking methods, all of which can change the glucose response. Even reputable summaries point out that meal GI may not predict individual post-meal responses as well as you might expect.
High GI is not automatically “bad” for everyone. For example, in endurance sport, faster carbohydrate availability can be a feature, not a bug. The question is context: healthy person at rest vs athlete mid-race vs someone trying to prevent hypoglycemia on insulin.
Suggested visual: glycemic index examples chart (bar chart).
Alt text: “Bar chart of glycemic index values for common foods, grouped into low, medium, and high GI categories.”
Data you can plot (GI values are approximate and vary by brand, ripeness, and cooking): baked russet potato ~111, cornflakes ~79, white bread ~71, sucrose ~63, banana ~55, apple ~39, lentils ~29.
Fiber and resistant starch: carbs that don’t act like “carbs”
Fiber is where many carb debates collapse, because fiber is a carbohydrate, but it behaves differently than sugars and starch. Many fibers resist digestion in the small intestine and reach the colon, where microbes can ferment them. Fermentation produces SCFAs like acetate, propionate, and butyrate, which are absorbed and influence gut barrier function and host metabolism.
A more useful way to think about fiber than “soluble vs insoluble” is:
Viscous fibers: thicken the contents of the gut, slow gastric emptying and nutrient absorption, and can help blunt post-meal glucose rises.
Fermentable fibers: feed gut microbes and increase SCFA production.
Bulking fibers: resist fermentation and help stool bulk and laxation.
Resistant starch sits in the middle: it is “starch” structurally, but it resists small-intestine digestion and acts more like fiber, reaching the colon for fermentation. Food processing and preparation can shift resistant starch content, which helps explain why the same “carb food” can behave differently depending on how it’s made.
On intake targets, many authorities converge on a similar fiber range. The Adequate Intake used in the Dietary Reference Intakes is 14 g fiber per 1,000 kcal (often summarized as ~25 g/day for women and ~38 g/day for men at typical energy intakes). Diabetes nutrition guidance also references at least this level.
Carbs, weight management, and chronic disease risk
Weight management: carbs are rarely the true lever
If “carbs and weight loss” has felt confusing online, it’s because two things can be true at once:
Reducing carbs can reduce calories and improve glycemia for some people.
Carbs themselves are not uniquely fattening compared with dietary fat when calories are matched.
A clean example is the DIETFITS randomized trial: adults assigned to a healthy low-fat vs healthy low-carb diet for 12 months lost weight in both groups, with no statistically significant difference in average weight loss between groups, and large person-to-person variability. The “healthy” part mattered: both approaches emphasized whole foods and minimized refined carbs and added sugars.
Metabolic ward evidence is also useful here because it controls intake tightly. In an isocaloric, inpatient crossover study, restricting dietary fat led to greater body fat loss than restricting carbohydrate over the short term, even though carbohydrate restriction increased fat oxidation. Translation: the body adapts, and simplistic “insulin equals fat gain” stories do not consistently predict fat loss when calories are controlled.
Diabetes and cardiovascular risk: quality dominates quantity
For diabetes, current standards emphasize individualization. Nutrition therapy is framed as a core part of care, and one-size-fits-all macro prescriptions are avoided. Importantly for this article, the standards explicitly support emphasizing nutrient-dense foods (non-starchy vegetables, whole fruits, legumes, whole grains, nuts/seeds) while minimizing refined grains, sweets, and sugar-sweetened beverages. They also note that reducing carbohydrate intake can be considered for some adults to improve glycemia, and they highlight processed-food reduction as a practical method.
For cardiovascular health, the 2021 scientific guidance stresses patterns: plenty of fruits and vegetables, foods made mostly with whole grains rather than refined grains, minimize added sugars, and prefer minimally processed foods. It also links added sugars with increased risk of type 2 diabetes, coronary heart disease, and excess body weight.
When you zoom out to long-term outcomes, the consistent theme is carbohydrate quality. Large analyses link higher intakes of dietary fiber and whole grains with lower risk of cardiovascular disease, type 2 diabetes, and all-cause mortality. Benefits often cluster around intakes in the 25–29 g/day range, with evidence suggesting additional benefit at higher intakes for some outcomes.
Glycemic index and load sit in the “useful but not complete” bucket. Observational and interventional evidence is mixed across endpoints, but higher GI patterns have been associated with higher cardiovascular risk in large datasets, and GI/GL are often most informative when paired with fiber and refinement level (for example, high GI plus low cereal fiber).
A quick word on free sugars: the World Health Organization recommends keeping free sugars below 10% of total energy across the life course, with a conditional suggestion to go below 5% for additional benefit, especially for dental caries outcomes. “Free sugars” includes sugars added to foods plus sugars naturally present in honey, syrups, fruit juices, and juice concentrates.
Practical carb targets and portioning for real diets and real people
General macro targets exist to give a starting point, not a personality test. The Dietary Reference Intakes set an adult carbohydrate RDA of 130 g/day (based on the brain’s minimum glucose use) and an Acceptable Macronutrient Distribution Range (AMDR) of 45–65% of total calories.
Here are practical ranges that work across many dietary preferences:
Baseline maintenance (mixed diet): Many people land comfortably around 45–55% of calories from carbs, with adequate protein and fats, emphasizing minimally processed sources. The AMDR simply says 45–65% is compatible with adequacy for most healthy adults.
Weight loss: The carb number is less important than (1) calorie deficit, (2) higher protein, (3) high-fiber carbs, and (4) a pattern you can keep doing. Trials show healthy low-carb and healthy low-fat can both work; adherence and food quality tend to drive outcomes.
Athletic performance: Carb needs scale with training volume and intensity. sports nutrition literature commonly cites rough ranges of ~3–12 g/kg/day, depending on the sport and training load, and emphasizes timing around training for glycogen support.
Diabetes (type 1 or type 2): Emphasis is on individualized planning, carb quality, and alignment with medications and glucose monitoring. Standards explicitly allow consideration of lower-carb approaches for some adults to improve glycemia, without declaring a single best carb percentage for everyone.
Keto / very low-carb: A ketogenic pattern typically keeps carbs very low (often <50 g/day in practice), but “keto” is not a uniform medical protocol outside specific clinical uses. If someone uses keto for appetite control or glycemia, fiber, micronutrients, LDL response, and sustainability become the key checkpoints. Evidence syntheses show mixed cardiometabolic effects and highlight variability in LDL response.
Portioning examples without obsessive math
If you want a simple portioning approach that adapts to vegetarian, vegan, omnivore, low-carb, or higher-carb training diets:
Start with fiber and protein, then “add carbs.” Build a plate around non-starchy vegetables plus a protein source (beans/lentils/tofu/eggs/fish/meat). Add a carb source (fruit, whole grain, starchy veg) based on your goal and glucose tolerance. This aligns with diabetes guidance emphasizing non-starchy vegetables, legumes, whole fruits, and whole grains while minimizing refined grains and sweets.
Use “carb blocks” (≈15 g net carb) if you like structure. One small piece of fruit, one slice of bread, 1/3 cup cooked rice, or 1/2 cup beans often clusters around this range, but labels and measurements vary. Carb counting is especially relevant when medications can cause hypoglycemia.
Aim for a fiber floor. If you change carb quantity, try not to let fiber collapse with it. The 14 g/1,000 kcal heuristic is a useful checkpoint, and higher intakes often correlate with better cardiometabolic outcomes in large analyses.
Life stages and sex-specific considerations
Carb needs are not identical across life stages, even if the internet pretends they are. Pregnancy is the clearest example. The Institute of Medicine target for pregnancy is commonly summarized as ≥175 g/day of carbohydrate, and recent reviews discuss concerns about going below that threshold during pregnancy, especially given fetal glucose needs and the complexity of gestational diabetes management.
Aging shifts the carb conversation too. Average insulin sensitivity tends to decline with age, although body composition and activity level are major mediators. In practice, older adults often benefit from prioritizing nutrient density, protein adequacy, and fiber-rich carbs that support bowel function and cardiometabolic health, while minimizing refined carbohydrate sources that can spike glucose with low satiety.
On sex-specific physiology: menstrual cycle hormones can alter insulin sensitivity modestly in some women, often with lower insulin sensitivity in the luteal phase in certain datasets, though results vary and effects are not identical for everyone. Translation: some people notice predictable glucose changes across the cycle, especially in diabetes contexts, and may need flexible carb and medication strategies rather than rigid daily targets.
Myths about carbs that don’t survive actual evidence
Myth: “Carbs make you fat.”
Weight gain is driven by sustained energy surplus, not a single macronutrient. Controlled trials comparing healthy low-carb and healthy low-fat patterns often show similar average weight loss, and metabolic ward data do not consistently support the idea that carbs uniquely drive fat gain when calories are matched. Carb quality and calorie density are usually the practical issues, not “carbs” as a category.
Myth: “Your brain can’t function without carbs, so everyone needs high carb.”
The brain uses glucose heavily, and adult carbohydrate RDA is based on the brain’s minimum glucose use. But under low-carb conditions, the brain can partially use ketone bodies. That does not mean everyone should go low-carb; it means the body has backup systems. The better question is what carb level supports your health goals, training, and glycemic stability.
Myth: “GI tells you which carbs are healthy.”
GI measures glucose response under standardized conditions, but mixed meals, fiber content, and individual differences can change the response. Many guidelines treat GI/GL as optional tools, while emphasizing minimally processed carbs, whole grains, legumes, vegetables, and limiting added sugars.
Myth: “Fruit is basically candy.”
Whole fruit comes packaged with water, fiber, micronutrients, and a slower eating rate. Health-oriented dietary patterns and diabetes guidance commonly include whole fruits while discouraging sugar-sweetened beverages and sweets. If glucose control is a concern, portioning and pairing fruit with protein or fat can help, but “avoid fruit” is usually an overcorrection.
Myth: “All sugars are equally harmful at any dose.”
Dose and delivery matter. The American Heart Association and other authorities focus heavily on limiting added sugars and sugar-sweetened beverages because they add calories with low satiety and can worsen cardiometabolic risk factors. Mechanistically, high sugar intakes (especially high fructose exposure in certain contexts) can increase hepatic de novo lipogenesis and triglycerides, but that is a very different claim than “any sugar ruins metabolism.”
Start Tracking with Makko
Put these insights into action. Track your calories, monitor your progress, and reach your goals.
Try Makko Free for 30 Days